How the Multi-Directional Reach Test Calculator Works
The Multi-Directional Reach Test (MDRT) measures your
limits of stabilityThe furthest you can lean in a direction before you must step or fall to stay upright. Reaching probes how far your center of mass can travel over your feet under control.
in four directions — forward, backward, right, and left — by seeing how far you can reach with an outstretched arm while keeping your feet planted. It extends the forward-only Functional Reach Test, and it exists for a simple reason: falls don’t only happen forward. People also fall sideways and backward, so a test that only measures forward reach misses part of the picture.
Roberta Newton developed it in 2001 as a portable, low-cost way to measure stability in both the
front-to-back and side-to-sideIn clinical terms, the anterior-posterior (forward/backward) and medio-lateral (left/right) directions — the two planes in which standing balance is usually described.
directions. All it needs is a yardstick set level at shoulder height — mounted on a wall or on a tripod — and a clear, safe space.
Step 1: Measure Four Reaches
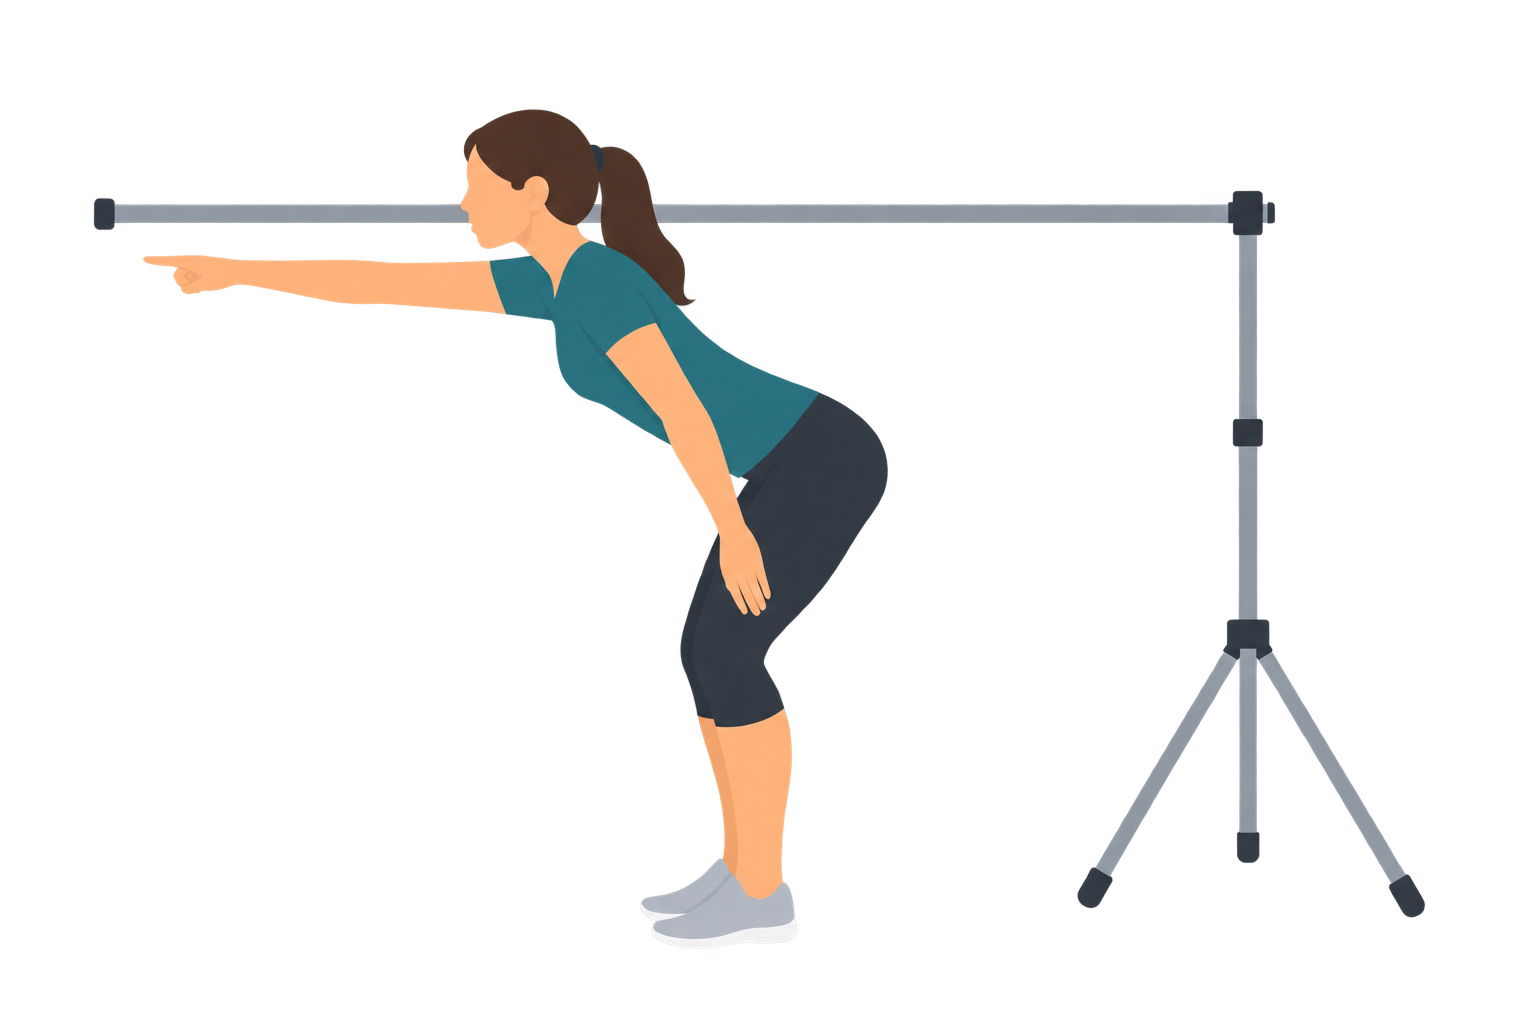
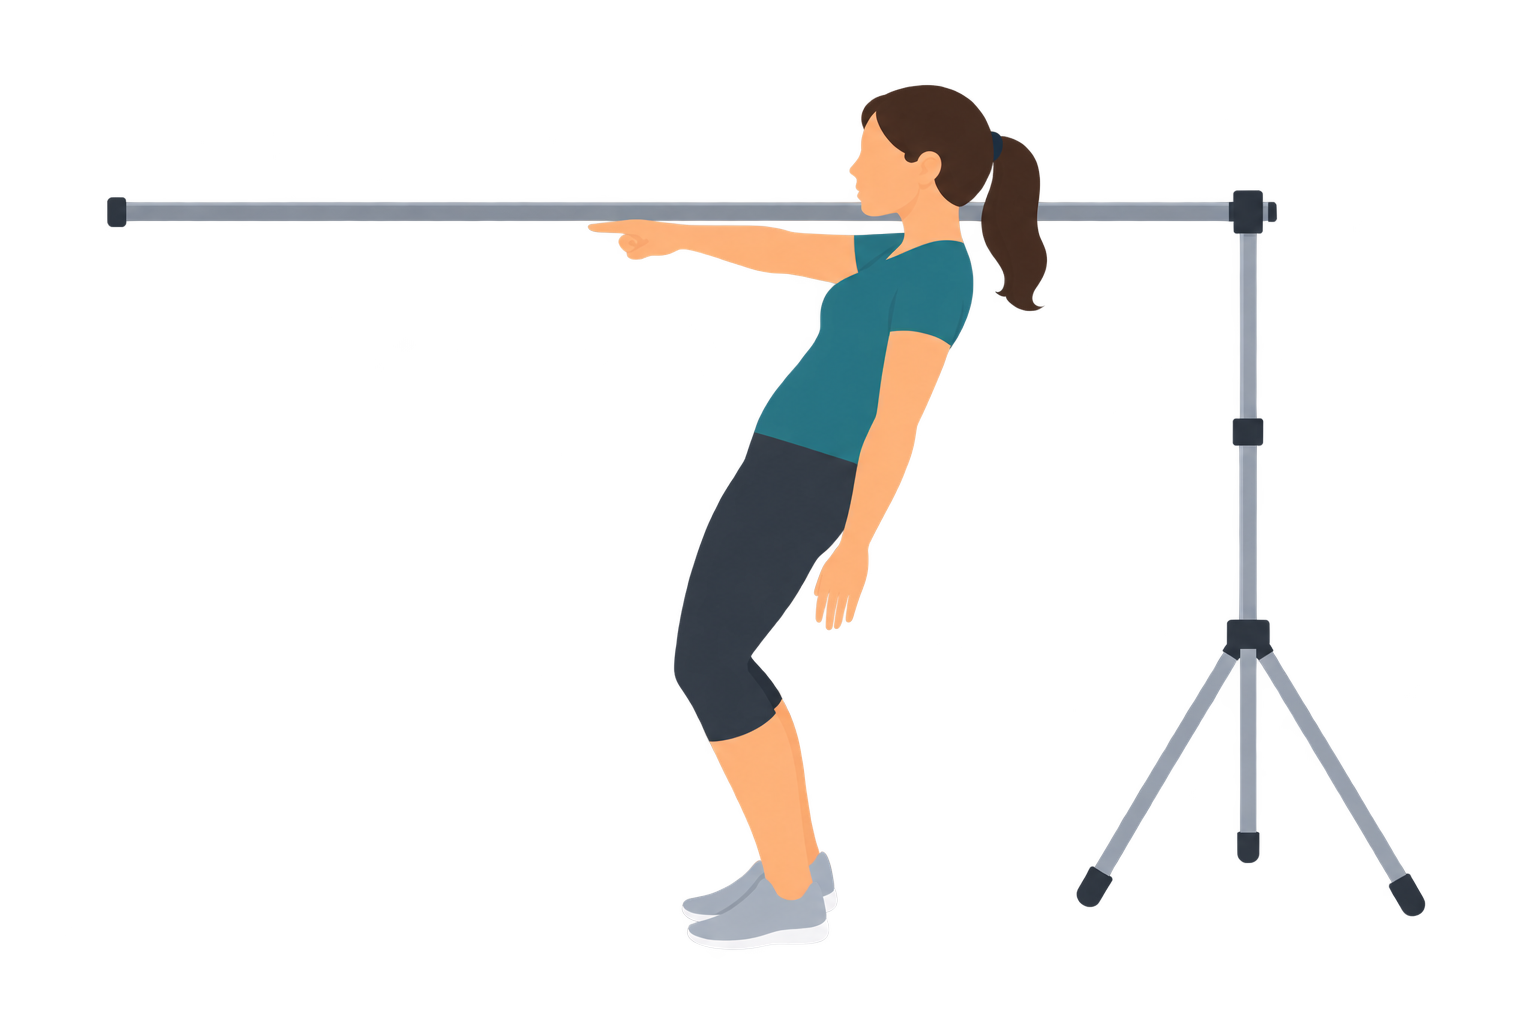
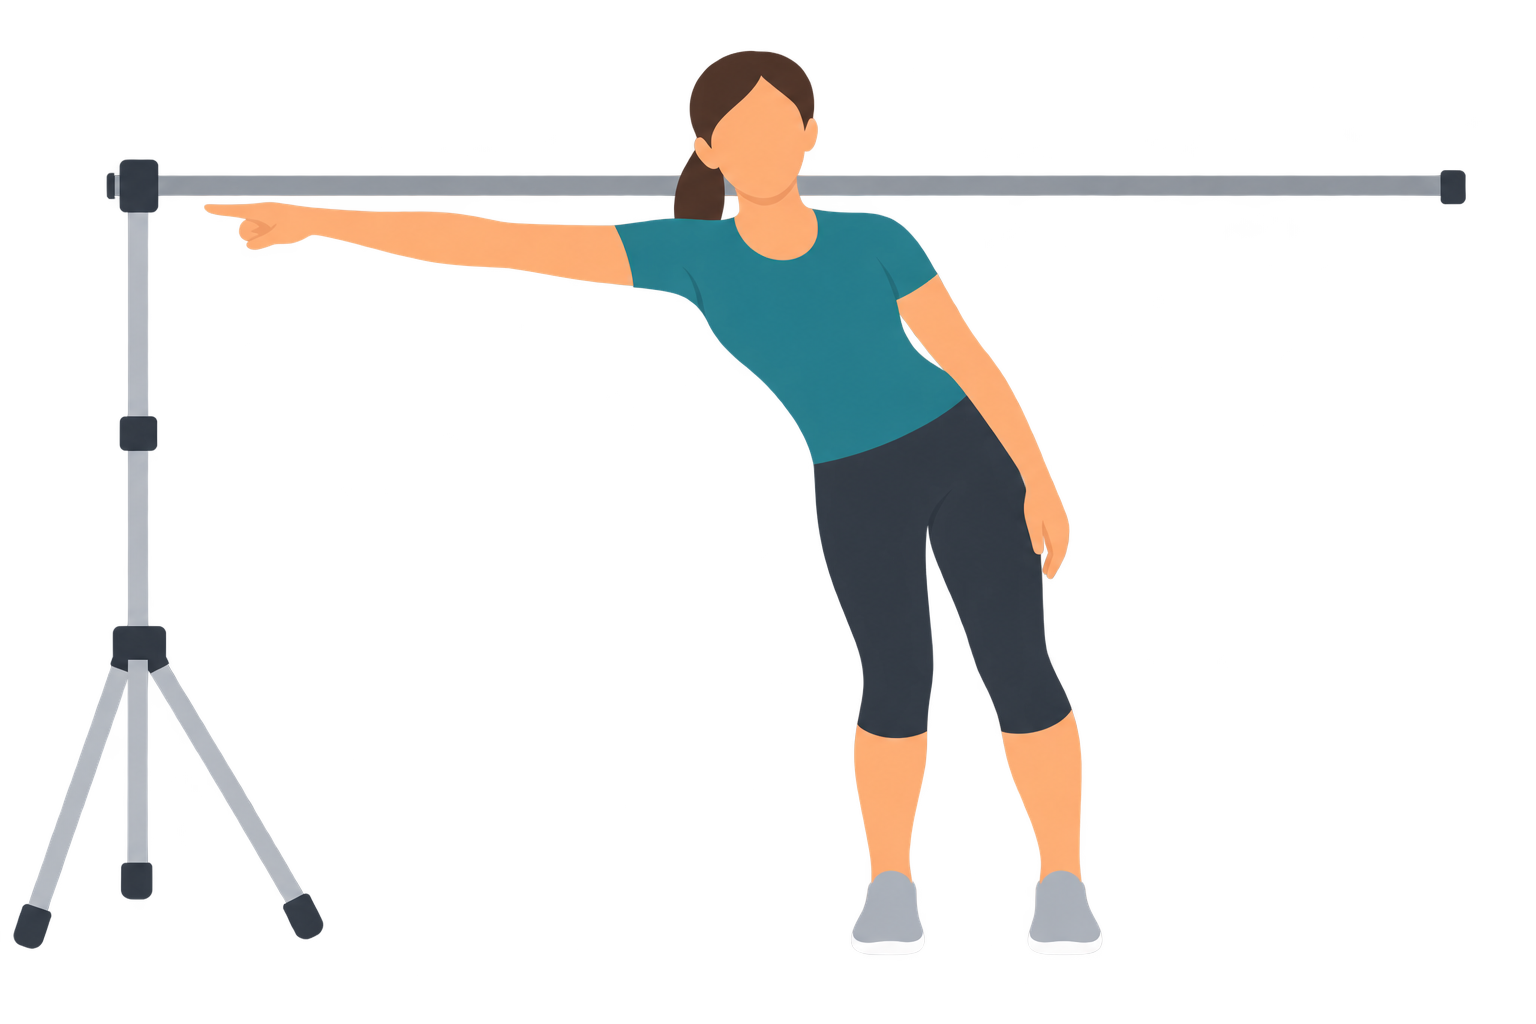
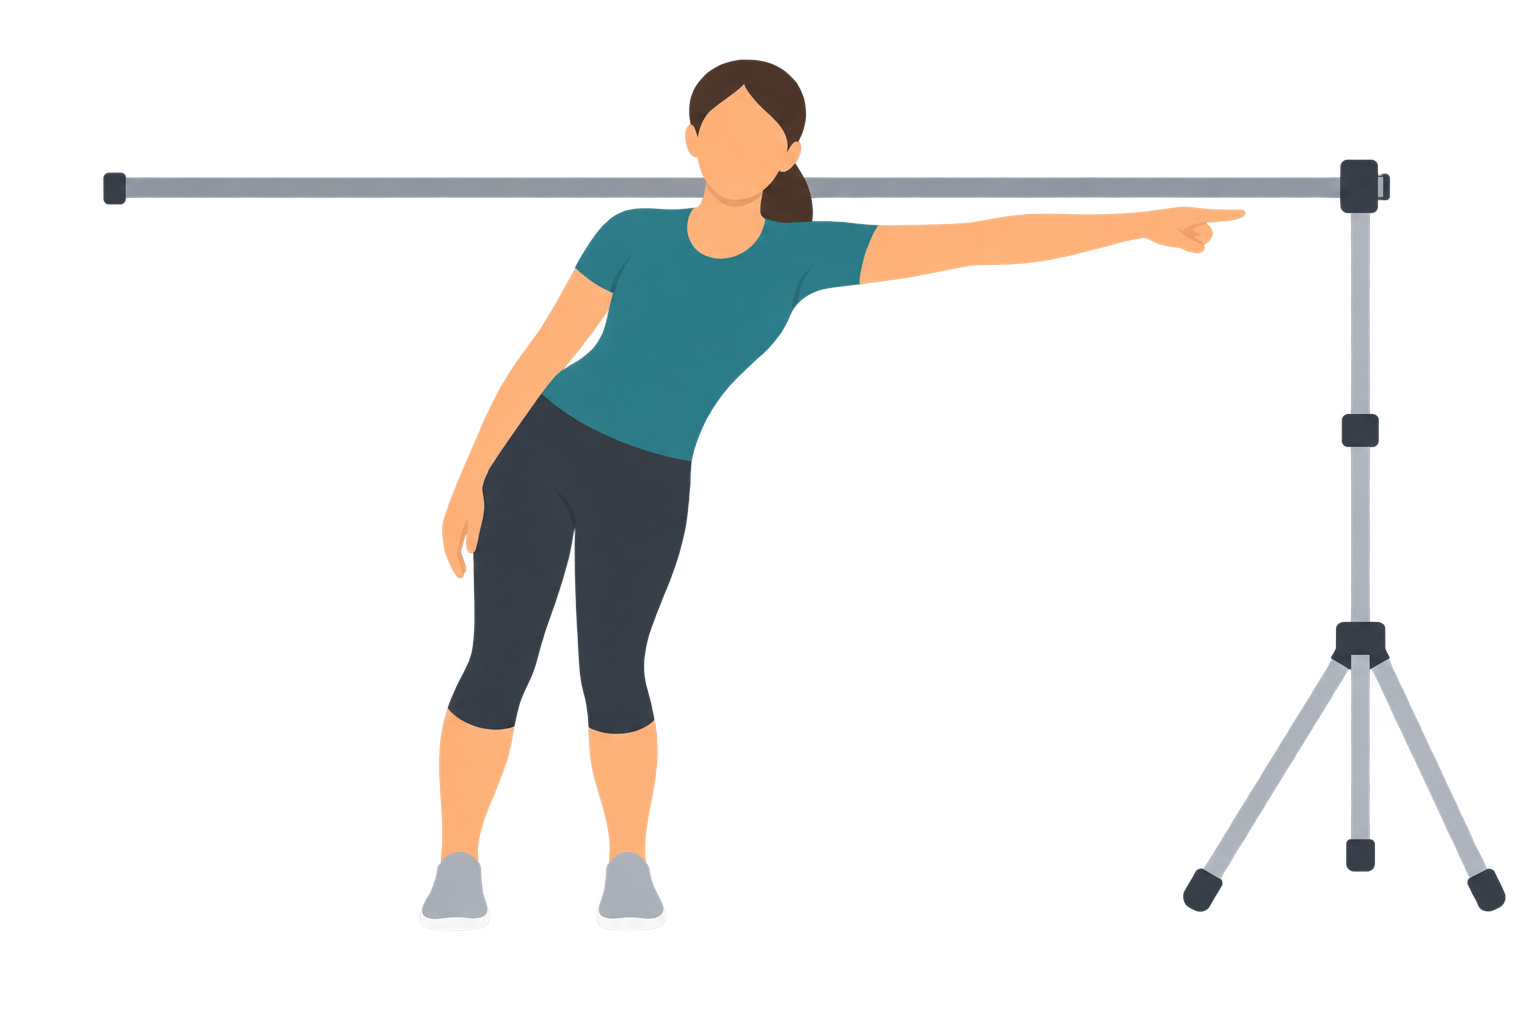
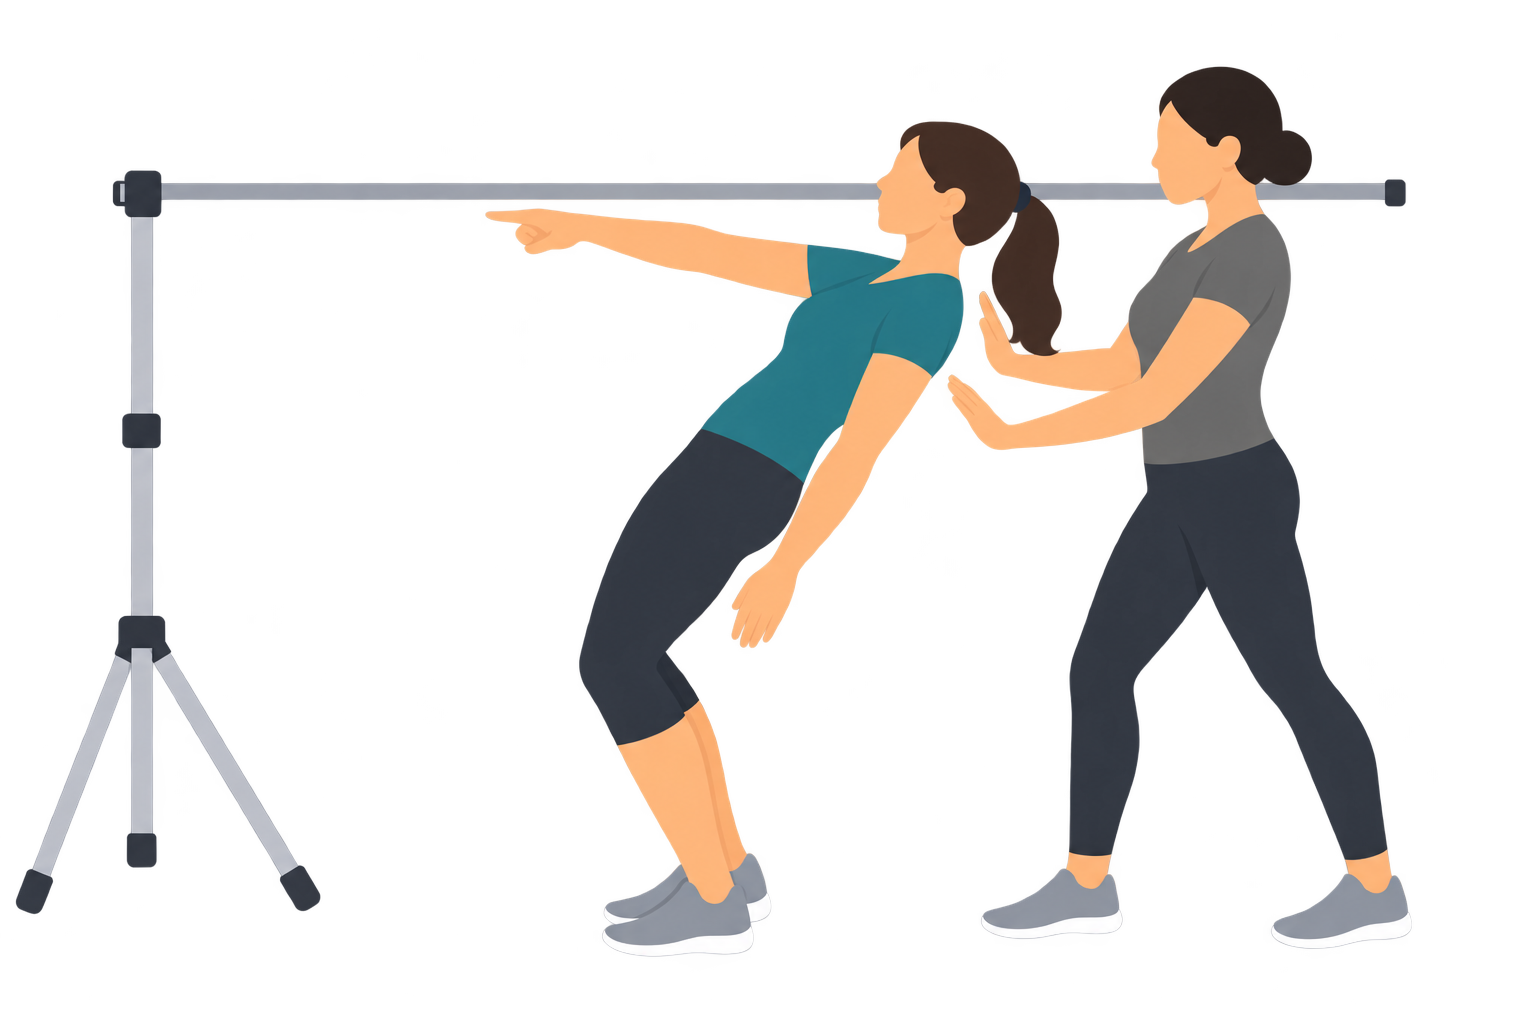
- Stand with your feet flat on the floor, a comfortable distance apart, beside a yardstick set level at shoulder height — mounted on a wall or on a tripod.
- Read the same hand landmark every time. Newton measured total hand excursion without specifying one, and clinical descriptions vary — index fingertip, middle fingertip, or a closed fist. Pick one and keep it identical across all four directions and every retest. (Note it differs from the Functional Reach Test, which reads the middle knuckle.)
- Use whichever arm you prefer for the forward and backward reaches, and the matching arm for each side — right arm reaching right, left arm reaching left.
- For each direction in turn — forward, straight backward (leaning back), right, and left — note your start position, reach as far as you can with the outstretched arm, and note where you end up.
- Keep your feet flat: no stepping, no lifting a heel or toe, no touching anything for support. If your feet move, discard that trial and take it again.
- The reach is the distance traveled. Use the average of two trials in each direction.
Reach (each direction) = end position − start position
Step 2: Compare Each Direction to the Norms
Each of your four reaches is compared to the average for healthy older adults, allowing for the normal spread around that average (one
standard deviationA measure of how much scores vary around the average. Roughly two-thirds of people fall within one standard deviation of the mean.).
Each direction is then labeled:
- Above typical — reaching further than most older adults.
- Within typical range — around the older-adult average.
- Below typical — noticeably under the average.
- Well below typical — far under the average, the clearest flag for reduced stability in that direction.
Left vs. Right: The Symmetry Check
Healthy people reach about equally far to the left and right, so the calculator compares your two lateral reaches and notes which is greater and by how much. A clear or repeatable side-to-side difference — or one side that lands in a worse band than the other — can point to a one-sided limitation. There is no validated asymmetry cut-off for this test, so it’s offered as a prompt to look closer, not a result in itself.
Why There’s No Single Score
You won’t see the four reaches blended into one number. That’s deliberate: in the original research the directions were found to measure related but distinct aspects of balance, and a forward limitation means something different from a backward or sideways one. Averaging them away would hide exactly the information the test was built to reveal. So each direction is reported on its own.
An Older-Adult Reference
The reference values come from community-dwelling older adults, pooled together rather than split by age or sex, because that is the group the validated norms describe. A healthy younger adult will reach well past these averages and land in the “above typical” band in every direction — which is expected, not remarkable. The comparison is most meaningful for older adults and for tracking change over time.
How This Differs from the Functional Reach Test
The forward reach here is not the same number you’d get from our standalone Functional Reach Test page. The two tests come from different studies, with different samples and slightly different setups, so their forward averages differ — Newton’s older-adult forward reach is shorter than the value in the Functional Reach Test’s norms. That’s why this calculator reads all four directions against Newton’s own consistent data, rather than borrowing the forward figure from the other page. Use the standalone test for a quick forward-only check against full-lifespan norms, and this one for a four-direction picture against older-adult norms — but don’t compare the numbers across the two.
Reading the Radar and the Table
- Reach Profile (radar) — your four reaches plotted on a compass: forward at the top, backward at the bottom, right and left to the sides, with the older-adult average overlaid as a dashed outline. A direction where you fall short shows as a dent in the shape.
- Direction Breakdown (table) — your reach, the older-adult average, and the status band for each direction.
What Affects Your Reaches
- Activity level — In the original study, how active a person was helped explain their forward and sideways reaches.
- Fear of falling — The same study found the backward reach was the one most tied to fear of falling — leaning back feels riskier, so anxiety shortens it independently of true balance.
- Strength and mobility — Hip and knee muscle strength and trunk mobility set how far you can lean with control.
- Body proportions — Longer arms add reach, another reason the result is read against norms rather than as an absolute distance.
Data Sources
- Newton RA (2001). “Validity of the multi-directional reach test: a practical measure for limits of stability in older adults.” Journal of Gerontology: Medical Sciences, 56A(4):M248–M252. Source of the four-direction reference values (254 community-dwelling older adults), with reliability above 0.92.
- Duncan PW, et al. (1990). The Functional Reach Test, which the MDRT extends from one direction to four.
- Note: later work has reported MDRT values across a wider age range (roughly 20–79), but this calculator uses Newton’s validated older-adult reference, which remains the standard citation.
Limitations and Important Caveats
- It is a screen, not a prediction. Reaching within the typical range does not guarantee you won’t fall, and a short reach does not confirm you will. It is one piece of a balance picture, usually combined with other tests.
- The norms are older adults only. There are no age- or sex-specific bands in the reference used here, so it isn’t designed to rate children, adolescents, or to finely distinguish younger adults.
- Setup and technique matter. A different start position, a lifted heel, or a sit-down version all change the numbers; consistency is what makes repeat tests comparable.
- One moment in time. A single test is a snapshot; a trend across sessions is more informative, especially through training or rehabilitation.
Disclaimer:
This calculator scores the Multi-Directional Reach Test against published older-adult reference values. It is for general informational and screening purposes only and is not a medical assessment, a diagnosis, or a prediction of falls. Always test in a safe space with sturdy support within reach and someone nearby to guard, and stop if you feel unsteady. The reference values describe community-dwelling older adults and may not apply to you; a result on this test should not, on its own, drive conclusions about your balance or decisions about activity. If you have balance concerns, dizziness, frailty, or a history of falls, consult a qualified healthcare provider. This tool does not replace professional assessment.